


Safety evaluated in 2 large clinical studies1
Adverse reactions (all grades) reported in ≥2%a of participants receiving YEZTUGO in both PURPOSE 1 or PURPOSE 21
No serious ISRs occurred in either PURPOSE 1 or PURPOSE 2 through 52 weeks
| Adverse reaction | PURPOSE 1 | PURPOSE 2 | ||
|---|---|---|---|---|
| YEZTUGO N=2140 |
FTC/TDFb N=1070 |
YEZTUGO N=2183 |
FTC/TDFb N=1088 |
|
| ISRs | 69% | 34% | 83% | 69% |
| Nodule | 64% | 17%c | 63% | 39% |
| Pain | 31% | 24%c | 56% | 53% |
| Induration | 4% | <1%c | 16% | 10% |
| Swelling | 4% | 5%c | 7% | 10% |
| Pruritus | 2% | 1%c | 3% | 3% |
| Erythema | 1% | 1%c | 17% | 19% |
| Bruising | <1% | <1%c | 3% | 4% |
| Warmth | <1% | <1%c | 2% | 2% |
| Headache | 7% | 8% | 2% | 2% |
| Nausea | 5% | 11% | 2% | 4% |
| Dizziness | 4% | 6% | <1% | 1% |
| Vomiting | 4% | 7% | <1% | 1% |
| Diarrhea | 4% | 4% | 2% | 2% |
| PURPOSE 1 | ||
|---|---|---|
| Adverse reaction |
YEZTUGO N=2140 | FTC/TDFb N=1070 |
| ISRs | 69% | 34% |
| Nodule | 64% | 17%c |
| Pain | 31% | 24%c |
| Induration | 4% | <1%c |
| Swelling | 4% | 5%c |
| Pruritus | 2% | 1%c |
| Erythema | 1% | 1%c |
| Bruising | <1% | <1%c |
| Warmth | <1% | <1%c |
| Headache | 7% | 8% |
| Nausea | 5% | 11% |
| Dizziness | 4% | 6% |
| Vomiting | 4% | 7% |
| Diarrhea | 4% | 4% |
| PURPOSE 2 | ||
|---|---|---|
| Adverse reaction |
YEZTUGO N=2183 | FTC/TDFb N=1088 |
| ISRs | 83% | 69% |
| Nodule | 63% | 39% |
| Pain | 56% | 53% |
| Induration | 16% | 10% |
| Swelling | 7% | 10% |
| Pruritus | 3% | 3% |
| Erythema | 17% | 19% |
| Bruising | 3% | 4% |
| Warmth | 2% | 2% |
| Headache | 2% | 2% |
| Nausea | 2% | 4% |
| Dizziness | <1% | 1% |
| Vomiting | <1% | 1% |
| Diarrhea | 2% | 2% |
aFrequencies of ARs are based on all AEs attributed to study drug (or to the procedure for injection site reactions) by the investigator.
bParticipants received placebo subcutaneous injections (polyethylene glycol 400).
cIncludes participants who received either FTC/TDF or FTC/TAF (N=3205).
Majority of ISRs were mild or moderate and incidence rates decreased with subsequent injections1

Adapted with permission from Bekker et al. N Engl J Med. 2024.

Adapted with permission from Kelley et al. N Engl J Med. 2025.
dInjection site nodule, pain, and swelling were the most commonly reported ISRs. Of these, Grade 3 ISRs reported in the YEZTUGO group: nodule (n=1; <0.1%); FTC/TDF group: pain (n=1; <0.1%).
eParticipants receiving placebo injections were either receiving FTC/TAF or FTC/TDF.
fInjection site nodule, pain, and erythema were the most commonly reported ISRs. Of these, Grade 3 ISRs reported in the YEZTUGO group: pain (n=4; 0.2%) and erythema (n=3; 0.1%); FTC/TDF group: pain (n=1; <0.1%).
gParticipants receiving placebo injections received FTC/TDF.

Lower incidence of any ISR reported with thigh vs abdomen1,6
In randomized, blinded phase (RBP) and open-label extensions (OLE)
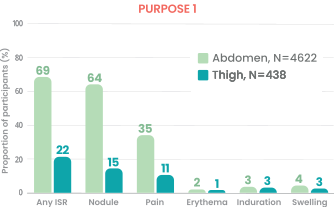
Safety and tolerability by injection site (Abdomen | Thigh): Any ISR: 69% | 21.7%; Any Grade 3 or 4 ISR: 0.2% | 0.7%; Any serious ISR: 0% | 0%; ISR leading to premature drug discontinuation: 0.1% | 0%.
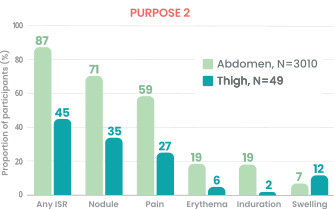
Safety and tolerability by injection site (Abdomen | Thigh): Any ISR: 87.3% | 44.9%; Any Grade 3 or 4 ISR: 0.6% | 0%; Any serious ISR: <0.1% | 0%; ISR leading to premature drug discontinuation: 0.9% | 0%.
ISR frequencies across RBP and OLE of PURPOSE 1 and PURPOSE 2 trials: After the 52-week RBP, participants who opted into the OLE either continued on YEZTUGO injections, or switched from oral FTC/TDF or FTC/TAF to YEZTUGO injections after initiation dosing, for an additional 52 weeks. Across the RBP and OLE, participants from PURPOSE 1 and PURPOSE 2 received YEZTUGO in at least 1 injection site. Study populations for both PURPOSE 1 (AGYW) and PURPOSE 2 (CGM, TGW, TGM, and GNB) were HIV-1 negative. Thigh injections during the RBP were limited to 32 individuals on YEZTUGO who became pregnant in PURPOSE 1, and for whom abdomen injections may not have been possible. “Any ISR” is reflective of all ISRs reported, including those other than the 5 most commonly reported ISRs presented in the graphs.
In both graphs, percentages are rounded to the nearest whole number.

Actor portrayals.
Drug interactions
Please see the full Prescribing Information for more details on drug interactions with YEZTUGO.
Strong or moderate inducers of CYP3A may significantly decrease plasma concentrations of lenacapavir, which may reduce the effectiveness of YEZTUGO. Dosage modifications are recommended when initiating these inducers. See dosage modifications.
Combined P-gp, UGT1A1, and strong CYP3A inhibitors may significantly increase plasma concentrations of YEZTUGO. Concomitant administration with YEZTUGO is not recommended.
YEZTUGO is a moderate inhibitor of CYP3A and a P-gp inhibitor that may increase the concentrations of coadministered sensitive substrates of CYP3A and P-gp, and increase risk of their adverse events. See the prescribing information of these sensitive substrates for dosing recommendations or appropriate monitoring of safety. YEZTUGO may increase the exposure of drugs primarily metabolized by CYP3A initiated within 9 months after the last subcutaneous dose of YEZTUGO.

HIV prevention done in your office
YEZTUGO is a twice-yearly, every-6-months subcutaneous injectable administered in your office.1

Multiple ways to acquire YEZTUGO
There are several ways your office may acquire YEZTUGO for the individuals in your care.
AEs=adverse events; AGYW=Adolescent girls and young women; ARs=adverse reactions; Bsl=baseline; CGM=cisgender men; GNB=gender nonbinary; ISRs=injection site reactions; FTC/TAF=emtricitabine/tenofovir alafenamide fumarate; FTC/TDF=emtricitabine/tenofovir disoproxil fumarate; P-gp=permeability glycoprotein; TGM=transgender men; TGW=transgender women; Wk=week.
Important Safety Information
BOXED WARNING: RISK OF DRUG RESISTANCE WITH USE OF YEZTUGO IN UNDIAGNOSED HIV-1 INFECTION
- Individuals must be tested for HIV-1 infection prior to initiating YEZTUGO, and with each subsequent injection of YEZTUGO, using a test approved or cleared by the FDA for the diagnosis of acute or primary HIV-1 infection. Drug-resistant HIV-1 variants have been identified with use of YEZTUGO by individuals with undiagnosed HIV-1 infection. Do not initiate YEZTUGO unless negative infection status is confirmed. Individuals who acquire HIV-1 while receiving YEZTUGO must transition to a complete HIV-1 treatment regimen.
Contraindications
- YEZTUGO is contraindicated in individuals with unknown or positive HIV-1 status.
Warnings and precautions
- Comprehensive risk management:
- Use YEZTUGO to reduce the risk of HIV-1 acquisition as part of a comprehensive prevention strategy including adherence to the administration schedule and safer sex practices, including condoms, to reduce the risk of sexually transmitted infections (STIs).
- HIV-1 acquisition risk includes behavioral, biological, or epidemiologic factors including, but not limited to, condomless sex, past or present STIs, self-identified HIV risk, having sexual partners of unknown HIV-1 viremic status, or sexual activity in a high-prevalence area or network. Counsel individuals on the use of other prevention methods to help reduce their risk.
- Use YEZTUGO only in individuals confirmed to be HIV-1 negative. Evaluate for current or recent signs or symptoms consistent with HIV-1 infection. Confirm HIV-1 negative status prior to initiating, prior to each subsequent injection, and as clinically appropriate.
- Potential risk of resistance:
- There is a potential risk of developing resistance to YEZTUGO if an individual acquires HIV-1 before or when receiving YEZTUGO, or following discontinuation. HIV-1 resistance substitutions may emerge in individuals with undiagnosed HIV-1 infection taking only YEZTUGO, because YEZTUGO alone is not a complete regimen for HIV-1 treatment.
- To minimize this risk, it is essential to test before each injection and additionally as clinically appropriate. Individuals confirmed to have HIV-1 must immediately begin a complete HIV-1 treatment regimen.
- Alternative forms of PrEP should be considered after discontinuation of YEZTUGO for those who are at continuing risk of HIV-1 acquisition and should be initiated within 28 weeks of the last YEZTUGO injection.
- Long-acting properties and potential associated risks:
- Residual concentrations of YEZTUGO may remain in systemic circulation for up to 12 months or longer after the last injection.
- Select individuals who agree to the required injection dosing schedule because nonadherence or missed doses could lead to HIV-1 acquisition and development of resistance.
- Serious injection site reactions: Improper administration (intradermal injection) has been associated with serious injection site reactions, including necrosis and ulcer. Only administer YEZTUGO subcutaneously.
Adverse reactions
- Most common adverse reactions (≥5%) in YEZTUGO clinical trials were injection site reactions, headache, and nausea.
Drug interactions
- Strong or moderate CYP3A inducers may significantly decrease YEZTUGO concentrations. Dosage modifications are recommended when initiating these inducers.
- It is not recommended to use YEZTUGO with combined P-gp, UGT1A1, and strong CYP3A inhibitors.
- Coadministration of YEZTUGO with sensitive substrates of CYP3A or P-gp may increase their concentrations and result in the increased risk of their adverse events. YEZTUGO may increase the exposure of drugs primarily metabolized by CYP3A initiated within 9 months after the last injection of YEZTUGO.
Dosage and administration
- HIV screening: Test for HIV-1 infection prior to initiating, prior to each subsequent injection, and as clinically appropriate using an approved or cleared test for the diagnosis of acute or primary HIV-1 infection.
- Dosage: Initiation dosing (injections and tablets) followed by once-every-6-months continuation injection dosing. Tablets may be taken with or without food.
- Initiation: Day 1: 927 mg by subcutaneous injection (2 x 1.5-mL injections) and 600 mg orally (2 x 300-mg tablets). Day 2: 600 mg orally.
- Continuation: 927 mg by subcutaneous injection every 6 months (26 weeks) from date of last injection ±2 weeks.
- Anticipated delayed injections: If scheduled 6-month injection is anticipated to be delayed by more than 2 weeks, YEZTUGO tablets may be taken on an interim basis (for up to 6 months) until injections resume. Dosage is 300 mg orally (1 x 300-mg tablet) once every 7 days. Resume continuation injections within 7 days of the last oral dose.
- Missed injections: If more than 28 weeks have elapsed since the last injection and YEZTUGO tablets have not been taken, restart with initiation dosing if clinically appropriate.
- Dosage modifications of YEZTUGO are recommended when initiating with strong or moderate CYP3A inducers. Consult the full Prescribing Information for recommendations.
Indication
YEZTUGO is indicated for pre‑exposure prophylaxis (PrEP) to reduce the risk of sexually acquired HIV-1 in adults and adolescents (≥35 kg) who are at risk for HIV-1 acquisition. Individuals must have a negative HIV-1 test prior to initiating YEZTUGO.
Please see full Prescribing Information for YEZTUGO, including BOXED WARNING.
References:
- YEZTUGO. Prescribing information. Gilead Sciences, Inc.; 2025.
- Bekker LG, Das M, Abdool Karim Q, et al; PURPOSE 1 study team. Twice-yearly lenacapavir or daily F/TAF for HIV prevention in cisgender women. N Engl J Med. 2024;391(13):1179-1192.
- Bekker LG, Das M, Abdool Karim Q, et al; PURPOSE 1 study team. Twice-yearly lenacapavir or daily F/TAF for HIV prevention in cisgender women. Supplementary Appendix. N Engl J Med. 2024;391(13):S1-S68.
- Kelley CF, Acevedo-Quiñones M, Agwu AL, et al; PURPOSE 2 study team. Twice-yearly lenacapavir for HIV prevention in men and gender-diverse persons. N Engl J Med. 2025;392(13):1261-1276.
- Kelley CF, Acevedo-Quiñones M, Agwu AL, et al; PURPOSE 2 study team. Twice-yearly lenacapavir for HIV prevention in men and gender-diverse persons. Supplementary Appendix. N Engl J Med. 2025;392(13):S1-S70.
- Brites C, Losso MH, Gallardo-Cartagena J, et al. Favorable tolerability of lenacapavir for PrEP administered at participant-chosen anatomic sites in PURPOSE 1 and PURPOSE 2. Poster presented at: AIDS 2026, the 26th International AIDS Conference; July 26-31, 2026; Rio de Janeiro, Brazil.